
High-Alert Medications: The Four That Hurt People Most
High-alert medications cause more serious harm than others when something goes wrong, and four groups matter most: insulin, heparin, opioids, and potassium. The rules the exam repeats are that only regular insulin can be given IV and units are never abbreviated, heparin needs aPTT and platelet monitoring with protamine as its antidote, opioids need respiratory and sedation checks with naloxone as antidote, and potassium is never given IV push.

The high-alert medications and the double-check habits that keep insulin, heparin, opioids and potassium safe.
From the Intensive NCLEX Course. See the course; the full video library is part of Pro and Ultimate.
Some drugs cause more serious harm than others when something goes wrong. These are called high-alert medications.
The exam tests them heavily because errors with them are dangerous.
Four groups matter most: insulin, heparin, opioids, and potassium.
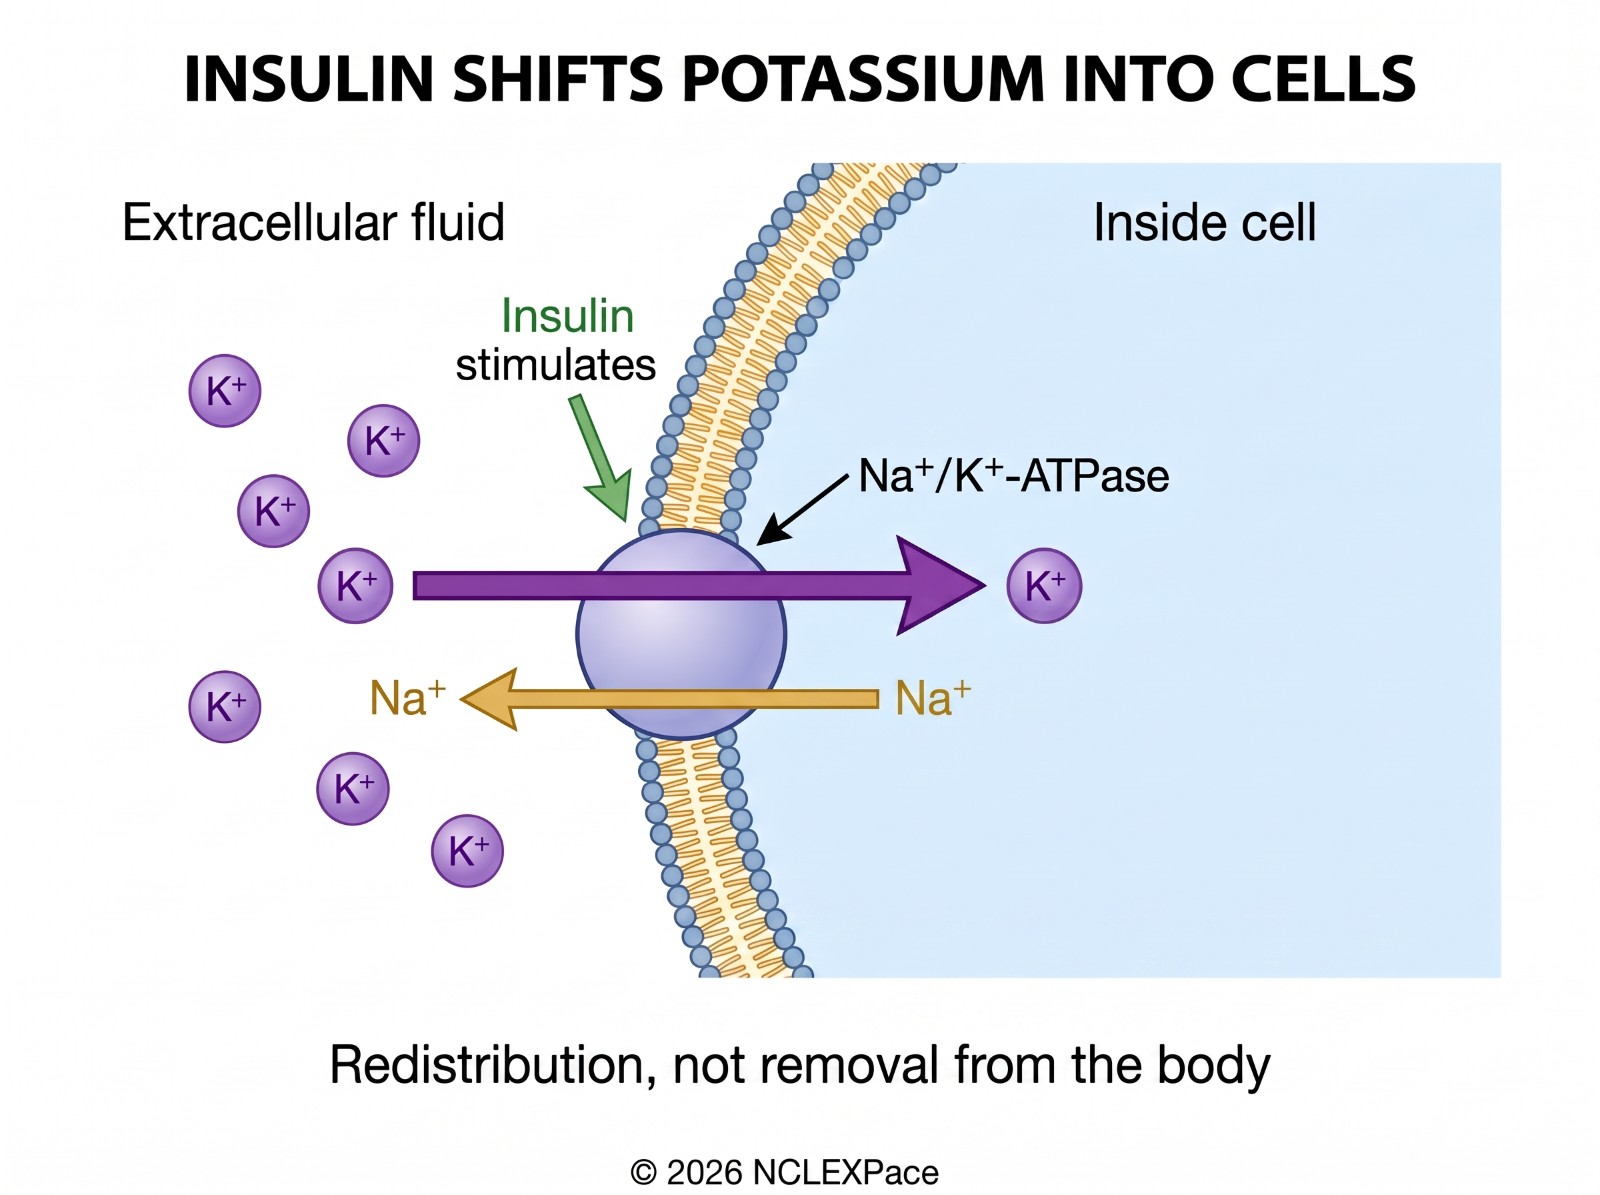
Insulin
Why it is dangerous: too much causes low blood sugar, which can cause seizures, brain damage, and death within minutes.
Safety rules:
- Use an insulin syringe only. Units, not mL.
- Two nurses verify the dose where policy requires it.
- Never abbreviate “units” as U. A “U” can look like a zero. 4U can be read as 40.
- Check blood sugar before giving, per orders.
- Only regular insulin can be given IV. No other type.
- Know when it peaks — that is when low blood sugar is most likely.
Signs of low blood sugar: shaky, sweaty, fast heart rate, hungry, confused, irritable, headache. Later: seizure, unconscious.
Treatment: if awake and able to swallow, give 15 grams of fast carbohydrate (juice, glucose tablets). Recheck in 15 minutes. If not awake, IV dextrose or glucagon.
Heparin
Why it is dangerous: too much causes bleeding, which can be fatal.
Safety rules:
- Two nurses verify the dose and pump settings.
- Check the lab — aPTT for IV heparin.
- Watch platelets. Heparin can cause a serious drop in platelets with clotting. A falling platelet count must be reported.
- Watch for bleeding: bruising, bleeding gums, blood in urine or stool, black stools, headache, back pain, drop in blood pressure.
- Antidote: protamine sulfate.
For subcutaneous heparin and low molecular weight heparin (enoxaparin):
- Give in the abdomen, at least 2 inches from the belly button
- Do not aspirate
- Do not rub the site
- For prefilled enoxaparin syringes, do not expel the air bubble
Opioids
Why they are dangerous: they slow breathing. Too much stops breathing.
Safety rules:
- Check respiratory rate before and after. Usually hold if breathing is under 12 per minute — follow the parameters given.
- Check sedation level. Increasing sleepiness comes before slowed breathing. It is the earlier warning sign.
- Watch for constipation — it happens to almost everyone. Treat it early.
- Antidote: naloxone.
Important: naloxone works fast but wears off faster than many opioids. The client can slip back into respiratory depression. Keep monitoring.
Potassium
Why it is dangerous: given wrong, it stops the heart.
The rules that are always tested:
- NEVER give potassium by IV push. This is fatal. There is no situation where it is correct.
- Always dilute and give as an infusion.
- Never add potassium to a bag that is already hanging. It does not mix evenly and the client can get a concentrated dose.
- Use a pump.
- Give slowly. Common limits are around 10 mEq per hour through a peripheral IV, higher only with cardiac monitoring in a monitored setting. Follow your facility’s policy.
- Check urine output first. If the client is not making urine, potassium builds up. Report low output before giving.
- Watch the IV site — potassium irritates veins and burns.
If a question offers “give potassium IV push” — it is always wrong.
The other high-alert groups
Also treated as high-alert in most facilities:
- Chemotherapy drugs
- Neuromuscular blocking agents (paralyze breathing — always with airway support)
- Concentrated electrolytes — potassium, hypertonic saline, magnesium
- Sedatives used in procedures
The three safety habits the exam wants
1. Independent double check. A second nurse checks the drug, dose, route, pump, and calculation separately — not just agreeing with you.
2. Question anything unclear. An unclear order, a strange dose, a hard-to-read handwriting. Stop and clarify. Never guess.
3. Do not give what you did not prepare. Unless you can fully verify it.
The short version
- Insulin: insulin syringe, units never abbreviated, only regular insulin IV, know the peak
- Heparin: check aPTT and platelets, watch bleeding, antidote is protamine
- Opioids: check breathing and sedation, antidote is naloxone, it wears off
- Potassium: never IV push, always dilute, never add to a hanging bag, check urine output
High-alert medication lists and infusion rate limits vary by facility. Follow your employer’s policy and check a current drug reference.
5 NCLEX practice questions on this topic
The same questions, player and partial-credit scoring students use inside NCLEXPace: answer, submit, read the full rationale, then Next. Your score is waiting at the end. No account needed for these.
A free account opens 20 more questions, a case study, a video and a cheat sheet. The full bank has 3,200+ questions with rationales, by topic.
Practice more, free →Ready for the full bank? See NCLEXPace plans and prices: one payment for 1, 2, 3 or 6 months.
Frequently asked questions
Common follow-up questions on Pharmacology.
What are the key safety rules for insulin?
Use an insulin syringe measured in units, never abbreviating units as U because it can look like a zero, and have two nurses verify the dose where policy requires. Only regular insulin can be given IV, and you should know when the insulin peaks because that is when low blood sugar is most likely. If blood sugar drops and the client can swallow, give 15 grams of fast carbohydrate and recheck in 15 minutes; if not awake, give IV dextrose or glucagon.
What is monitored with heparin?
Two nurses verify the dose and pump settings, and you check the aPTT for IV heparin and watch platelets, because heparin can cause a serious drop in platelets with clotting, so a falling platelet count must be reported. Watch for bleeding such as bruising, bleeding gums, blood in urine or stool, black stools, headache, and a drop in blood pressure. The antidote is protamine sulfate.
How are opioids given safely?
Check respiratory rate before and after and usually hold if breathing is under 12 per minute, following the parameters given. Check sedation level, because increasing sleepiness comes before slowed breathing and is the earlier warning sign, and watch for constipation. The antidote is naloxone, which works fast but wears off faster than many opioids, so the client can slip back into respiratory depression and needs continued monitoring.
Why is potassium never given by IV push?
Given wrong, potassium stops the heart, and IV push is fatal with no situation where it is correct. Always dilute it and give it as a slow infusion on a pump, never adding it to a bag that is already hanging because it does not mix evenly and the client can get a concentrated dose. Check urine output first, since potassium builds up if the client is not making urine, and watch the IV site because potassium irritates and burns veins.
What safety habits does the exam expect with high-alert drugs?
An independent double check, where a second nurse checks the drug, dose, route, pump, and calculation separately rather than just agreeing with you. Question anything unclear, such as an unclear order, a strange dose, or hard-to-read handwriting, and stop to clarify instead of guessing. And do not give what you did not prepare unless you can fully verify it.
Sources and references
- Potter PA, Perry AG, Stockert PA, Hall AM. Fundamentals of Nursing. 10th ed. Elsevier; 2021; Chapter: Medication Administration.
- Institute for Safe Medication Practices. ISMP List of High-Alert Medications in Acute Care Settings. ISMP; 2024.
Reviewed by the NCLEXPace team, October 2026.
Keep reading


3,200+ NCLEX questions with think-like-a-nurse rationales, unfolding case studies and adaptive readiness exams. Start with free practice questions, then choose a plan when you are ready.
Create Free Account →